
In vitro fertilization has become one of the most sophisticated, time-sensitive medical services in modern healthcare. While clinical capabilities have advanced genetic screening, improved ovarian stimulation strategies, and AI-assisted embryo grading, one bottleneck remains surprisingly unchanged across many clinics: appointment coordination.
IVF is a discipline of precision. Yet the administrative backbone supporting this precision is often fragmented, manual, and misaligned with the biological and emotional realities of fertility treatment. Poor coordination is not merely an inconvenience. It is a structural weakness that affects clinical outcomes, patient satisfaction, staff productivity, and ultimately the economic performance of the clinic.
As the fertility market becomes more competitive, appointment coordination has quietly shifted from a back-office task to a core strategic capability. And clinics that fail to upgrade this capability will increasingly fall behind.
Appointment Coordination: The Overlooked Variable in IVF Success
Most IVF centers view scheduling as an administrative function necessary, but not mission-critical. But when we analyze the IVF pathway, coordination sits at the intersection of every clinical and emotional moment.
A typical IVF cycle involves:
- Hormonal monitoring
- Ultrasound scanning
- Adjustments in medication doses
- Trigger administration
- Oocyte retrieval
- Embryo culture and transfer
- Follow-up consultations
Each step is tightly linked to the previous one. A delay in bloodwork reporting shifts a scan. A scan delay pushes trigger timing. A change in trigger timing affects retrieval, which directly influences oocyte maturity and embryology lab workflow. Thus, one missed or misaligned appointment has cascading effects across the entire treatment cycle.
This complexity is further compounded by the emotional volatility of IVF. Patients are balancing demanding medication routines, work commitments, financial stress, and uncertainty. When the clinic’s coordination appears inconsistent, patients immediately perceive it as a lack of care and that perception erodes trust quickly.
This is not theoretical. A cross-center study in the Netherlands involving 1,499 infertile women found that communication, timeliness, and coordination of care were among the lowest-rated aspects of the IVF experience, despite high clinical standards.
Source: Huppelschoten et al., Human Reproduction, 2013
The insight is clear:
Even highly skilled clinics are judged by their operational reliability as much as by their medical expertise.
Where Coordination Fails: The Anatomy of a Breakdown
Most coordination failures stem from one or more of the following structural issues:
- Fragmented Communication Channels
Many clinics still depend on phone calls, WhatsApp groups, sticky notes, or manual spreadsheets to coordinate complex medical workflows. When multiple departments, front desk, radiology, clinicians, and embryologists operate in silos, the probability of miscommunication increases.
- Unpredictable Patient Physiology
Ovarian response cannot be pre-programmed. Some patients respond faster to stimulation, others slower. Without a dynamic scheduling system, clinics must manually adjust appointments on short notice, often leading to chaos.
- Lab and Clinic Misalignment
The timing between the clinical team (trigger and retrieval) and the lab team (oocyte processing, fertilization, ICSI) is extremely sensitive. Even a one-hour delay can alter the maturity of retrieved oocytes, impacting fertilization and embryo development.
- Administration Under Pressure
Front-desk teams operate in high-stress environments, managing dozens of cycles simultaneously. Without automated guidance, errors are inevitable.
These challenges do not exist in isolation. Together, they form a coordination ecosystem that, if unmanaged, creates systemic risk.
Four Coordination Failures, and What Each One Costs
Coordination breakdowns are not random. They recur in the same four shapes, and each has a distinct cost.
1. The unanswered inbound call
A patient rings mid-morning to ask whether to take tonight’s dose after a delayed scan. The line is engaged; nobody calls back until the following day. The patient guesses.
Cost: a protocol deviation the clinic does not learn about, entered into no record, and discovered only if the next scan looks wrong. This is the failure mode an AI front desk is built for — inbound questions answered on WhatsApp or the clinic site at the moment they are asked, with anything clinical handed to a named human rather than guessed at.
2. The post-operative follow-up that nobody owns
After retrieval, the patient is told someone will call with fertilisation results. Which role makes that call is not defined, so it happens late or not at all.
Cost: the single most anxious wait in the cycle, extended for no clinical reason. This is also the point where patients most often start looking at other clinics.
3. The appointment that could not be moved
A monitoring scan needs to shift by a day. Doing that means checking clinician availability, ultrasound room availability, and whether the new date still sits inside the protocol window — three lookups across two systems.
Cost: either the appointment does not move and the patient travels at an inconvenient time, or it moves and breaks the monitoring interval. A cycle-aware scheduler resolves this because the constraint is encoded, not remembered: the system knows a Day 8 scan cannot slip past Day 9.
4. The reminder that never reached the patient
The appointment was booked correctly and confirmed at the desk three weeks earlier. Nobody confirmed it again.
Cost: a no-show that consumed a slot, a clinician, and a room. In a cycle-bound speciality that slot cannot be refilled at short notice.
Three of those four are communication failures, not booking failures — which is why coordination rarely improves by buying a better calendar. For the patterns that show up in patient messages before a coordination failure becomes a cancellation, see 9 messaging signals that turn IVF inquiries into confirmed cycles.
The Clinical Impact: Timing Errors Are Outcome Errors
IVF is governed by biological timing windows that cannot be stretched or negotiated. Poor coordination often results in one of the most consequential errors in the fertility process incorrect timing of oocyte retrieval.
A retrospective study by Basu et al. (2014) established that oocyte maturity significantly increases when retrieval is performed around 35 hours after the hCG trigger. Retrievals done earlier than this window yielded lower MII oocyte proportions, directly affecting fertilization and embryo quality.
Source: Basu et al., Journal of Human Reproductive Sciences, 2014
This illustrates a key principle of IVF operations:
A clinic’s scheduling accuracy directly affects its embryology outcomes.
When appointment coordination is manual:
- Trigger calls may be sent late
- Patients may misinterpret timings
- Retrievals may be scheduled at suboptimal hours
- Labs may be overwhelmed with poorly distributed cases
- Clinicians may need to rush or delay procedures
- Any of these deviations can compromise the clinical integrity of the cycle.
This is why leading IVF centers worldwide now treat appointment coordination not as administration, but as a critical scientific support function requiring equal rigor.
The Psychological Impact: Poor Coordination Amplifies Stress
Fertility treatment is emotionally demanding even under ideal conditions. Lack of timely communication, sudden schedule changes, or unclear instructions significantly worsen the emotional burden.
A 2016 study published in Fertility Research and Practice confirmed that longer waiting times and unclear coordination were strongly associated with lower satisfaction across IVF units, regardless of clinical competence.
Patients interpret poor coordination as disorganization—and disorganization feels unsafe during a fragile treatment journey.
High stress levels not only reduce patient satisfaction but, in some cases, may influence treatment adherence and perception of outcomes. In a market driven heavily by word-of-mouth, this emotional gap reflects directly in the clinic’s reputation.
The Business Impact: Coordination Is Becoming a Competitive Differentiator
For IVF clinics, operational inefficiency translates into tangible business risk:
- Unpredictable patient flow increases staff burnout.
- Communication errors invite complaints and reputation damage.
- Cycle cancellations reduce revenue and trust.
- Negative reviews deter high-value international patients.
- Scaling becomes difficult without proportional hiring.
In contrast, clinics using advanced IVF management software platforms like Meddilink and its IVF EMR module MedART benefit from:
- Real-time synchronization between clinical and lab teams
- Cycle-based scheduling that automatically adjusts to biological response
- Automated communication loops to reduce patient anxiety
- Predictable staff workloads and smoother peak-hour balancing
- Fewer missed or incorrectly timed triggers
- A more consistent and reliable overall patient journey
This operational reliability becomes a market advantage, especially in regions where patients have multiple clinic options.
Technology as the Solution: IVF Management Software as the Operational Nervous System
The emerging trend across leading global fertility centers is clear:
The future of IVF coordination will be automated, data-driven, and unified.
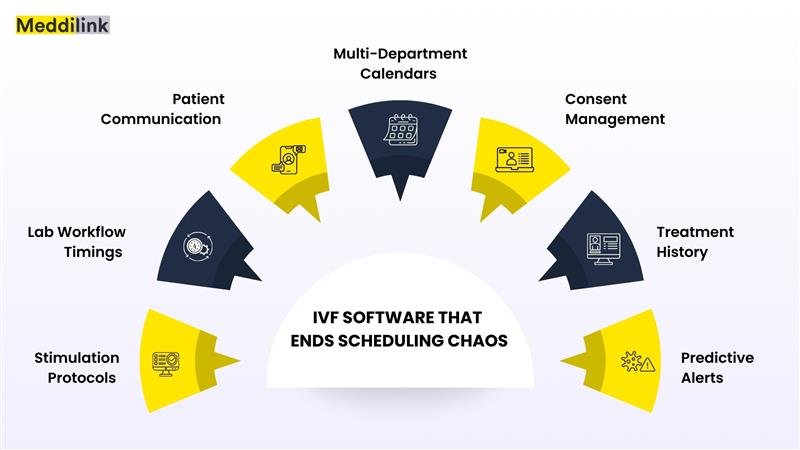
Modern IVF management software replaces manual scheduling with a real-time coordination engine that understands the medical context of each cycle. Platforms like MedART integrate:
- Stimulation protocols
- Lab workflow timings
- Patient communication
- Multi-department calendars
- Consent management
- Treatment history
- Predictive alerts
This transforms scheduling from a reactive task into a proactive system capable of anticipating delays, adjusting appointments, and reducing human error.
The result is a new coordination model:
clinically integrated, operationally seamless, and emotionally supportive.
Precision in Scheduling Is Now a Standard of Care
The next decade of IVF will not be defined solely by scientific breakthroughs. It will be defined equally by how well clinics manage complexity, communication, and timing.
Appointment coordination, which once seemed like a background function, has emerged as a powerful driver of clinical accuracy, patient trust, and business performance. Modernizing this function is no longer optional. It is essential for any clinic that wants to deliver high-quality, reliable, and emotionally supportive care.
Platforms like MedART enable that transformation by embedding precision and automation into every stage of the patient journey — with MedXbot handling the inbound communication layer where most coordination actually breaks, and the Scheduler module enforcing the cycle constraints that make a monitoring interval non-negotiable.
When coordination aligns with clinical science, IVF becomes safer, smoother, more predictable, and ultimately more successful.
In IVF, a single mistimed hour can change an outcome.
With the right systems, every hour can work in the clinic’s favor and the patient’s.
Topics

Product Implementation Lead · CSPO®, CSM®
Ravi Chhajed is a Product Implementation Lead specializing in healthcare SaaS, including EMR and IVF systems. He focuses on clinical workflow automation and AI-enabled product delivery. Ravi holds the Certified Scrum Product Owner (CSPO®) and Certified ScrumMaster (CSM®) certifications, bringing an agile approach to delivering and implementing clinical software.


